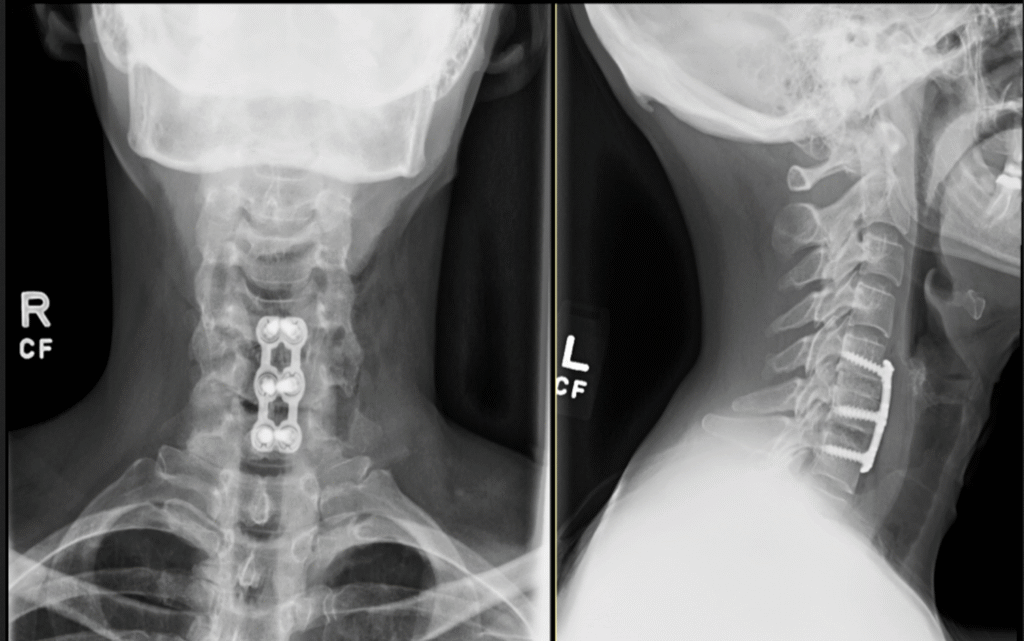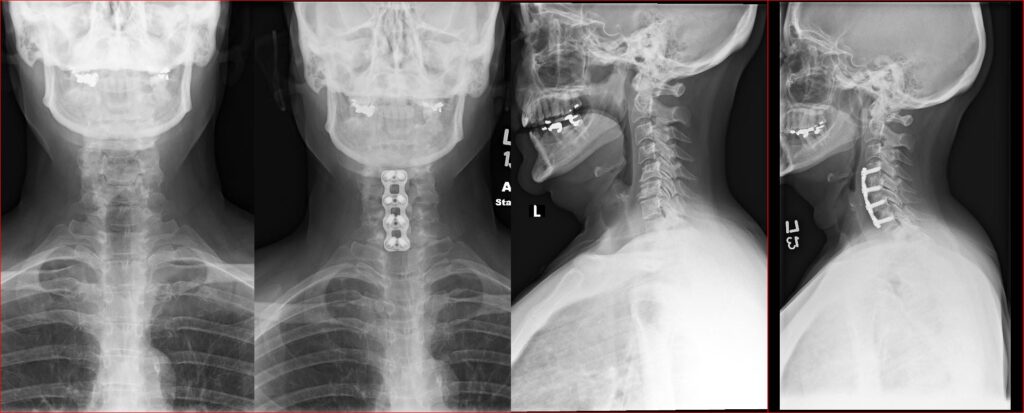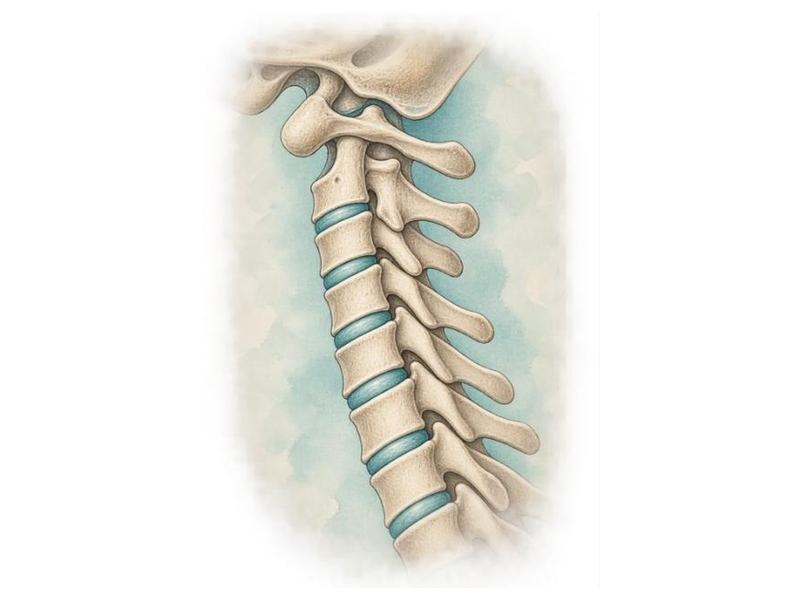
ACDF remains the standard when motion preservation is not safe or not possible. The disc is removed, the cord and roots are decompressed, and a cage or graft restores disc height. A plate holds the segment while it heals into one bone.
Dr. Li studies the details that affect fusion: cage subsidence in patients with sarcopenia, screw size and pseudarthrosis, and whether an ENT evaluation is warranted before revision ACDF. Those questions exist because a “routine” ACDF is only routine when the plan is right.
When one level needs fusion and an adjacent level can keep moving, a hybrid of ACDF and disc replacement is often a better reconstruction than fusing everything in sight.
What to expect
- A small anterior incision, typically in a skin crease.
- Overnight observation is common; some patients go home the same day.
- A brief period of swallowing discomfort is expected.
Recovery
- Fusion takes months, even if you feel better in days. Activity is advanced as imaging confirms healing.
- Smoking, poorly controlled diabetes, and osteoporosis slow fusion and are addressed before elective surgery whenever possible.